Medical History Form Template
A medical history form is a form that collects a patient's past diagnoses, surgeries, hospital stays, current medications, allergies and family history so a doctor or nurse can treat them safely without starting from scratch at the appointment. This template splits those questions into short pages, asks for medication doses and allergic reactions in the patient's own words, and closes with a consent statement.
- 20 questions
- 4 pages
- ~6 min
- To fill in
- Steps layout
- Mobile-ready
- Free
- No credit card
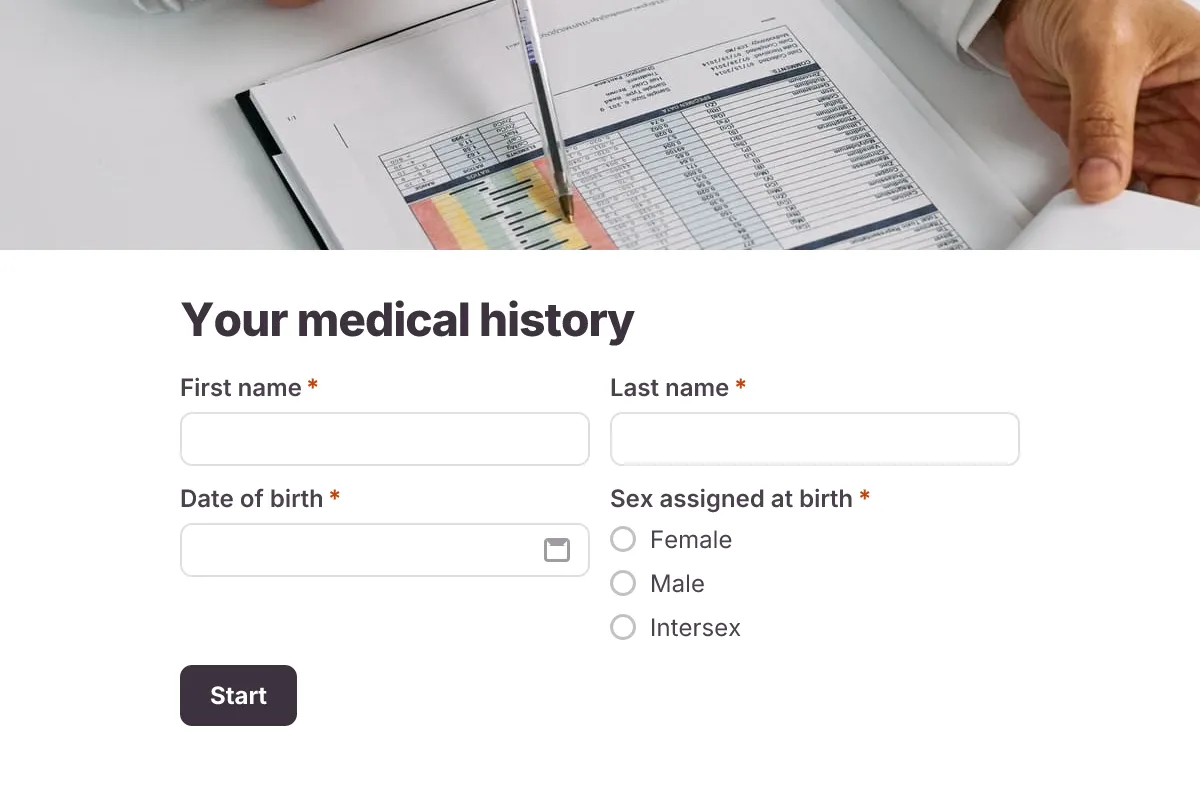
Live preview · nothing you type is sent
Photo by cottonbro studio on Pexels
Who it's for
Family practices, walk-in clinics, specialist consultants, dental offices, physiotherapy and chiropractic clinics, and occupational health teams registering new patients.
- New patients completing their history at home before a first appointment
- Annual review where returning patients update medications and new diagnoses
- Pre-operative assessment ahead of a day-surgery or dental procedure
- Occupational health screening for new employees in physical roles
What this template asks
Every question can be changed, removed or reordered once it's yours.
Patient details
First name*
Short text
Last name*
Short text
Date of birth*
Date
Sex assigned at birth*
Multiple choice
- Female
- Male
- Intersex
- Prefer not to say
Email*
Email
Phone number*
Phone number
Who is filling in this form?*
Multiple choice
- The patient
- Parent or guardian
- Carer or family member
Primary care doctor or clinic
Short text
Optional
Conditions and surgeries
Have you ever been diagnosed with any of these?
Checkboxes
Tick all that apply
- High blood pressure
- Heart disease
- Diabetes
- Asthma or COPD
- Thyroid disorder
- Kidney or liver disease
- Cancer
- Stroke or seizures
- Depression or anxiety
- Arthritis
- None of these
Other medical conditions
Long text
Optional. Include the year you were diagnosed
Past surgeries and hospital stays
Long text
Optional. Procedure, year and hospital, for example: appendix removed, 2015, City Hospital
Are you pregnant or could you be pregnant?
Multiple choice
Optional
- Yes
- No
- Not sure
- Not applicable
Medications and allergies
Do you take any medications, vitamins or supplements?*
Multiple choice
- Yes
- No
List each medication with its dose and how often you take it
Long text
For example: metformin 500 mg, twice a day
Do you have any allergies to medicines, foods, latex or anything else?*
Multiple choice
- Yes
- No
- Not sure
What are you allergic to, and what reaction did you have?
Long text
For example: penicillin, hives and swelling
Family history and lifestyle
Has a parent, brother or sister had any of these?
Checkboxes
- Heart disease before age 60
- Diabetes
- Cancer
- Stroke
- High blood pressure
- Mental health conditions
- None that I know of
Do you smoke or vape?*
Multiple choice
- Never
- Used to
- Occasionally
- Daily
How many alcoholic drinks do you have in a typical week?*
Multiple choice
- None
- 1 to 7
- 8 to 14
- More than 14
- Prefer not to say
Confirmation*
Checkboxes
- The information I have given is complete and correct to the best of my knowledge
Tips for more responses
- 1
Use conditional logic so the medication and allergy detail boxes only appear when a patient answers Yes.
- 2
Turn on save-and-resume so patients can stop to check pill bottles or ask a relative about family history.
- 3
Set up a PDF template so each completed history prints as a clean one-file record for the chart.
Questions
What should a medical history form include?
Patient identity and date of birth, current and past medical conditions, past surgeries and hospital stays, current medications with doses, allergies and the reaction they cause, family history of conditions such as heart disease, diabetes and cancer, lifestyle questions on smoking, alcohol and exercise, and a statement that the information is accurate.
Is it safe to collect medical history with an online form?
Responses and file uploads are stored privately and only people you give access to can see them. Health data is regulated differently around the world, so check your local health-privacy rules and your own policies before collecting patient information online.
How often should patients update their medical history?
Most clinics ask patients to review their history at least once a year and whenever they start a new medication, have surgery or receive a new diagnosis. Sending the same form link before an annual review is an easy way to do this.
Can a parent fill in the form for a child?
Yes. The form asks who is completing it, so a parent or guardian can answer for a child, or a carer for an adult who needs help.
Is this medical history template free?
Yes. Copy it into a free Dculus Forms account, change anything you like and start collecting responses. No credit card is needed.
Can I change the questions?
Yes. Your copy opens in the form builder, where you can add, remove and reorder questions, change the layout and add your own branding.
Where do the responses go?
Responses arrive in your Dculus Forms workspace. You can export them to Excel or CSV, send them to Google Sheets or a webhook, and get email notifications.
Can I host it myself?
Yes. Dculus Forms is open source (GPLv3), so you can run it on your own servers and keep every response in your own database.
Similar templates
All templates
Therapy Intake
Gather a new counseling client's reasons for seeking help, symptoms, history, safety screening, goals and informed consent.
- Intake
- Consent
- Multi-page
Healthcare · 20 questions · 5 min
Patient Intake Form
A new-patient form covering contact details, insurance, medical history, medications and consent.
- Clinic
- Intake
- Multi-page
Healthcare · 18 questions · 6 min
Summer Camp Registration
Register campers for summer camp: camper details, weeks, day type, pickup authorization, allergies, medication and parent consent.
- Registration
- Consent
- Multi-page
Education · 24 questions · 7 min